This one sounds like a film script: Four families from four corners of India, who had never met, brought together by the same desperate calculation — if they could not save their own, perhaps they could save each other’s.

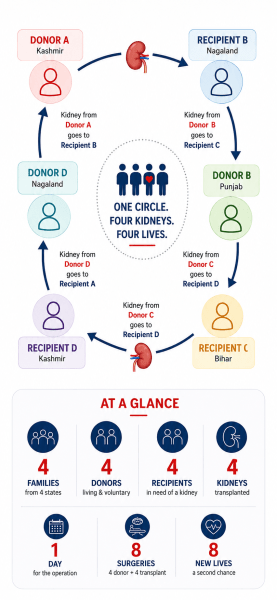
The families had found a possible answer: don’t give the kidney to the person you love. Give it to someone else’s loved one instead. Donor A would give to Recipient B. Donor B would give to Recipient C. Donor C would give to Recipient D. And Donor D would give to Recipient A. This was a circle of strangers, each saving a family they had never met, in the hope that another stranger would do the same for theirs. But there was another obstacle. The law.
This was a circle of strangers, each saving a family they had never met, in the hope that another stranger would do the same for theirs.
Why four pairs were so much harder to approve than two
Kidney-swap transplantation is not new in India. The basic idea is relatively simple: when a willing donor cannot donate to their intended recipient because of biological incompatibility, another donor-recipient pair can enter the exchange. The two donors effectively swap recipients.
The difficulty grows rapidly as more pairs are added. A transplant team has to establish not merely that each donor is compatible with somebody, but that the entire chain works. A kidney has to move in such a way that the chain closes.
Immunological testing is central to that process. Tests such as the single antigen bead, or SAB, test can identify antibodies in a recipient that may react against specific human leukocyte antigens on a prospective donor’s kidney. Previous pregnancies, blood transfusions and transplants can all contribute to sensitisation.
In a four-way exchange, there are many more possible combinations — and every link matters. “We have tried three-way swaps manually, but matching donors with unrelated recipients is a very tedious and complex task,” Dr Anant Kumar, who led the operation, told The Indian Express. For the four families who had already spent years waiting, the question was no longer simply whether a compatible kidney existed. It was whether the law would allow them to use it.
Crossing legal hurdles
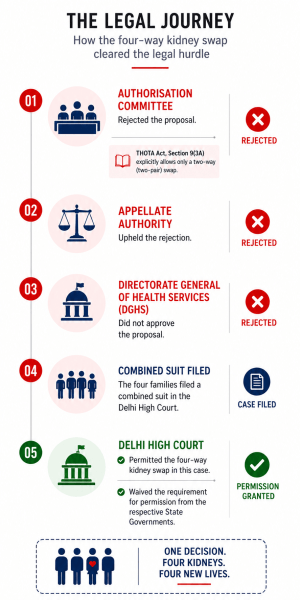
The proposal for a four-way kidney swap was rejected by the Authorisation Committee, a legal body established under India’s Transplantation of Human Organs and Tissues Act (THOTA). The Appellate Authority upheld that decision, taking the view that Section 9(3A) of THOTA only contemplated an exchange between only two incompatible donor-recipient pairs. A larger chain, the authorities held, would require an amendment to the law.
On May 26, 2026, the Delhi High Court stepped into that gap. In Shivani Khurana & Ors. v. Union of India & Ors., Justice Purushaindra Kumar Kaurav set aside the orders of the Authorisation Committee and the Appellate Authority. The court held that Section 9(3A) should not be read as restricting swap transplantation to two donor-recipient pairs. The references in the provision to a “first donor” and “second donor”, it held, were illustrative of the mechanism rather than a statutory ceiling on the number of pairs. There was, in other words, a gap between what the technology and medicine could make possible and what officials believed the wording of the law allowed.
The case was sent back to the Authorisation Committee for consideration of the four-way transplant in accordance with that interpretation, subject to the safeguards in the Act, including the requirement that there be no commercial dealing in organs. On July 13, 2026, eight people — four donors and four recipients — got admitted at Max Super Speciality Hospital, Saket. By the end of the day, four kidneys moved from one family to another.
The proposal for a four-way kidney swap was rejected by the Authorisation Committee.
A high-risk operation
The four-way swap had to be executed as one carefully choreographed chain. Eight operations were involved: four donor nephrectomies, in which kidneys were removed from the living donors, and four transplant operations. They were conducted simultaneously across five operating theatres, beginning at around 7 am and continuing until 6 pm. The matching itself had been worked out in advance using Alliance for Paired Kidney Donation software and then cross-checked through detailed immunological testing. Matching eight people on paper was only the beginning.
The eight patients were kept sedated in rooms close to one another. As a kidney was removed from one donor, it was placed in an ice bowl and rushed to the adjoining operating room, where the compatible recipient was already waiting. The next donor-recipient link was being prepared even as the previous transplant was taking place. There was no room for a break in the chain.
“Like in an army, responsibilities are divided man to man, post to post,” Dr Kumar said. “Here too, our team of doctors had divided the responsibility.”
The legal clock made the logistics even tighter. The High Court’s order had waived the requirement for separate approvals from each patient’s respective state government — a mandatory step under the usual process. “So, we only had a day for the operation to be done,” Dr Kumar said.
The operation became a medical relay race: while one team removed a kidney, another was preparing its recipient; while one transplant was under way, another donor was being brought towards the operating theatre.
What could have gone wrong
The risks were not isolated to one operation. A donor could have withdrawn. A recipient could have developed a medical problem. A delay in one operating theatre could have disrupted the sequence. And after the transplant, the chain would still not be over. Every recipient’s immune system had to accept the new organ.
“If, after such a procedure, the patient gets a fever, there can be complications,” Dr Kumar said. “If the kidney is rejected, then there could be issues – including a return to dialysis, or in the worst cases, loss of the transplanted organ altogether. Imagine Donor C develops an unexpected problem and cannot undergo nephrectomy. It potentially leaves the corresponding recipient without a kidney and breaks the chain involving the other families,” he added.
The donors don’t have kidney failure. They are healthy people voluntarily undergoing nephrectomy so somebody else can receive their kidney. So, the medical team has to balance the recipient’s urgent need against the safety of every donor.
Kidney transplantation in India remains constrained by a profound gap between the number of people who need kidneys and the number of organs available. Around 13,000–14,000 kidney transplants are performed annually, according to recent sources, with living donation accounting for the majority.
A paired exchange offers a possibility. A multi-way exchange expands it further. In this case, four families who began as strangers became dependent on one another. Each donor had to trust that another family would keep its part of the bargain. Each recipient’s chance at a new life depended on a kidney coming from somebody else’s loved one.

 Doctors with kidney recipients.

 This was a circle of strangers, each saving a family they had never met, in the hope that another stranger would do the same for theirs.
 The proposal for a four-way kidney swap was rejected by the Authorisation Committee.


 Share


